

Could about 10 g of carbohydrate per hour be enough to maintain blood glucose and preserve performance during prolonged exercise? Noakes and colleagues (2026) propose that hypothesis and bring the liver back into the discussion about fatigue. To see how far that number applies, we need to look at the effort it was tested on.
The review reinforces the role of blood glucose and liver glycogen in fatigue during prolonged exercise. Hypoglycemia remains a plausible primary mechanism. The 10 g/h dose rests mainly on a small, fasted trial that used placebo as the comparator. The design leaves its relevance to other athletes, sports, intensities, and durations open. Guidelines remain the starting point for practice.

The paper changes the question before changing the dose
Noakes and colleagues organized more than a century of research into 16 lines of evidence. Their review shifts the focus from muscle glycogen to circulating glucose and liver glycogen.
The authors hypothesize that when the liver can no longer replace glucose as quickly as it is used, the nervous system would reduce muscle recruitment and slow the pace before the brain’s glucose supply fell to dangerous levels. In this model, carbohydrate intake could help maintain blood glucose even while the muscles still have fuel.
Carbohydrate intake can improve endurance
Meta-analyses find average benefit, especially in longer efforts. The effect is usually greater in tests to exhaustion than in time trials.
Liver and blood glucose matter
Maintaining glucose availability for the nervous system and for prolonged exercise is a real part of the phenomenon, not a secondary detail.
Is falling blood glucose the main mechanism?
The association between falling blood glucose, fatigue, and the response to carbohydrate fits the hypothesis. The contributions of muscle glycogen, perceived exertion, heat, and other mechanisms remain open.
When was 10 g/h enough?
The result comes from a specific placebo-controlled protocol. The lowest effective dose in other settings and equivalence with higher doses remain open questions.
The contribution of the paper is to force science to take a better look at blood glucose. The mistake would be to transform this lens into single explanation.
‘Blood glucose fell’ is not automatically synonymous with clinical hypoglycemia
In their retrospective analysis, the authors treated any decrease of more than 0.1 mmol/L from the start of exercise as a sign of developing hypoglycemia. In most studies classified this way, the drop exceeded 0.3 mmol/L. The paper itself cites 3.9 mmol/L as a clinical reference threshold.
A drop from 5.2 to 5.0 mmol/L counts in this analysis even though blood glucose stays within the normal range. The trend may be physiologically relevant. Interpreting it also requires looking at the level reached and any symptoms.
Fasting, duration, intensity, liver glycogen, and carbohydrate intake can all affect both blood glucose and performance. The greater benefit from carbohydrate when blood glucose falls in the placebo group fits the authors’ hypothesis. Identifying the main cause of fatigue requires a design that can separate those factors.
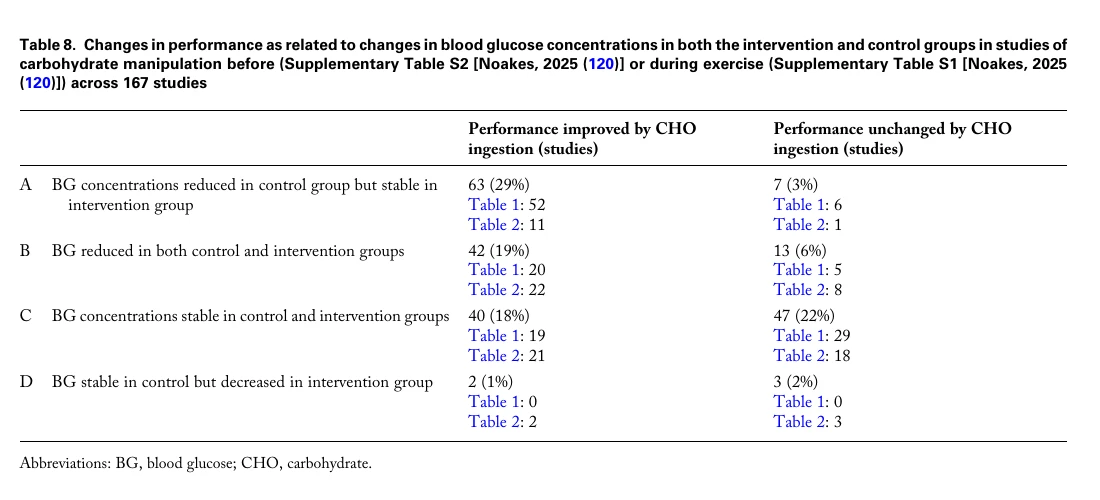
Two counts in Table 8 need an explanation
The table relates changes in blood glucose in the control and intervention groups to changes in performance.
What the table itself shows
Audit of published numbersThese discrepancies lower confidence in the numerical summary. The authors need to clarify whether they counted studies, conditions, or comparisons. The biological hypothesis remains open.
The supplementary material is public, which is a strength of transparency. At the same time, the review is narrative: it does not present a reproducible search strategy, duplicate selection, formal assessment of risk of bias, or meta-analysis with effect sizes. Counting heterogeneous studies is not equivalent to estimating the combined effect or controlling quality, sample size and dependence between comparisons.
Where do the 10 g/h come from?
In the randomized crossover trial by Prins and colleagues (2025), ten trained male triathletes completed two six-week periods, one on a high-carbohydrate diet and one on a very-low-carbohydrate diet. After fasting for about 15 hours, they cycled to exhaustion at 70% of VO₂max. The researchers compared placebo with approximately 10 g/h of maltodextrin.
A strong result within a narrow scenario
Prins and colleagues, 2025.
Compared with placebo, the authors reported that maltodextrin prevented blood glucose from falling below 3.9 mmol/L and increased time to exhaustion by about 22% on both diets.
Fasting was part of the design to investigate falling blood glucose. The 22% describes how much longer the athletes held that workload. Race speed was outside the scope of the test.
The trial also leaves its relevance to women, athletes who have eaten before exercise, time trials, and team sports open. Assessing equivalence with 30, 60, or 90 g/h, or identifying the lowest effective and optimal doses, would require direct comparisons with other doses.
How the ideas connect
What the broader syntheses show
Ramos-Campo and colleagues (2024) included 136 studies in their meta-analysis with meta-regression. On average, taking carbohydrate during exercise improved performance compared with placebo or control. The effect was larger in time-to-exhaustion tests and longer efforts, with some evidence of greater benefit in less-trained participants.
Dose did not significantly moderate the average effect. Differences between protocols, few studies within each dose range, and difficulty separating dose from context limit what we can conclude about dose equivalence or whether 10 g/h is optimal.
In the abstract of their 2026 review, Tarrit and colleagues report 15 reviews, 262 randomized trials, and 521 individual tests. The main text lists 525 tests in one passage and 264 studies in another. The findings were more favorable for efforts lasting one to four hours and for carbohydrate combinations. With 11 of the 15 reviews (73%) rated low or critically low in quality, the evidence is more useful for identifying where benefit is likely than for setting a dose.
In practice, the dose responds to the work
Use the Brazilian Sports Nutrition Association (ABNE) guideline as a starting point. Published in 2025 using GRADE, it recommends 30–60 g/h for efforts lasting more than 75 minutes and up to 90 g/h from mixed sources beyond 2.5 hours. The choice within those ranges depends on duration, intensity, the goal, gastrointestinal tolerance, and logistics.
| Scenario | More defensible reading | What 10 g/h does not resolve |
|---|---|---|
| Up to 60–75 min | The need during exercise is variable and depends on the initial state, intensity and objective. | They do not create an obligation when the session does not require fueling. |
| More than 75 minutes | The Brazilian guideline uses 30–60 g/h as a reference range, adjusted to the context. | They were not directly compared to this range in the key trial. |
| More than 2.5 hours | Up to 90 g/h of mixed sources can be considered, with progression and gastrointestinal training. | They are not shown to sustain increased competitive demand or subsequent recovery. |
| Team sports | Intermittent efforts, decision-making, breaks, and the competition schedule require their own interpretation. | They cannot be generalized from a continuous cycling test to exhaustion. |
| Athlete with symptoms | Document food intake, blood glucose when indicated, duration, intensity, and symptoms; investigate recurrence. | They do not replace clinical evaluation nor do they treat every cause of decreased performance. |
Ranges from the 2025 ABNE Clinical Practice Guideline. Application should be tested in training and adapted to the athlete, sport, and environment.
In training, look for the lowest dose that lets the athlete sustain the planned effort, is tolerable, and protects recovery and health.
Is 10 g/h enough? The right question is: for what effort?
- The paper changes the question before changing the dose
- Where do the 10 g/h come from?
- In practice, the dose responds to the work
What I would take into training and competition
- Define the demand before the dose.Duration, intensity, modality, prior nutrition, temperature, goal and recovery change the need.
- Separate maintaining blood glucose from supplying the entire system.Preventing hypoglycemia may be sufficient in one scenario; sustaining power, cognition, and recovery may require another strategy.
- Use the guidelines as a starting point.They structure the decision; they do not eliminate individualization or make the upper limit mandatory.
- Train the gut and the logistics.A dose only exists in practice when the athlete tolerates, transports and consumes it at the expected rate.
- Don't turn low intake into chronic low availability.Reducing carbohydrate during a session must not normalize low energy availability, inadequate recovery, or signs of REDs.
- Record the response.Pace, power, perception of effort, symptoms, blood glucose when clinically indicated and recovery help to review the strategy.
Conflicts of interest do not invalidate the paper — they raise the standard of scrutiny
The authors disclose ties to low-carbohydrate diet books and royalties, equity and consulting in companies linked to low-carbohydrate diets and metabolic health, and patents and commercial activities involving ketones. The review received open-access publishing support and acknowledges funding for some of the work that contributed to it.
Those ties warrant particular care when interpreting the findings, especially when studies by the same group carry weight in the conclusion.
ABNE considers it reasonable to question high doses as a general rule. It emphasizes that a narrative review is insufficient to establish hypoglycemia as the main cause of fatigue or to support carbohydrate restriction outside the individual context.
The hypothesis deserves testing. The dose deserves context
The review brings blood glucose, the liver, and the nervous system back into the discussion about fatigue, alongside muscle glycogen. Being able to tolerate or oxidize more carbohydrate does not, on its own, guarantee better performance.
The missing test is a direct comparison of doses in men and women, in fasted and fed conditions, in time trials and races. That means measuring blood glucose, liver and muscle glycogen, oxidation, nervous system responses, symptoms, and recovery.
Until then, test in training the strategy you plan to use on race day. Judge the dose by the effort you can sustain and by how you recover afterward.
Verified references
The main reference was confirmed in its final version; the full text, supplements, funding, declarations of interest, and editorial status were reviewed. No correction or retraction was identified as of August 16, 2026. The interpretation was checked against the 10 g/h trial, systematic syntheses, a clinical guideline, and the ABNE position statement. Editorial revision and source check on November 7, 2026.